
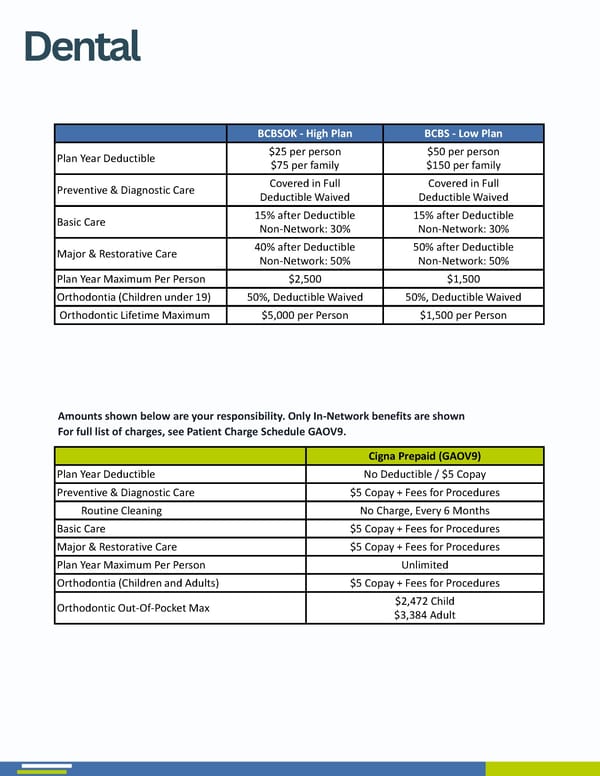
Amounts shown below are your responsibility . Only In - Network benefits are shown BCBSOK - High Plan BCBS - Low Plan Plan Year Deductible $25 per person $75 per family $50 per person $150 per family Preventive & Diagnostic Care Covered in Full Deductible Waived Covered in Full Deductible Waived Basic Care 15% after Deductible Non - Network: 30% 15% after Deductible Non - Network: 30% Major & Restorative Care 40% after Deductible Non - Network: 50% 50% after Deductible Non - Network: 50% Plan Year Maximum Per Person $2,500 $1,500 Orthodontia (Children under 19) 50%, Deductible Waived 50%, Deductible Waived Orthodontic Lifetime Maximum $5,000 per Person $1,500 per Person Cigna Prepaid (GAOV9) Plan Year Deductible No Deductible / $5 Copay Preventive & Diagnostic Care $5 Copay + Fees for Procedures Routine Cleaning No Charge, Every 6 Months Basic Care $5 Copay + Fees for Procedures Major & Restorative Care $5 Copay + Fees for Procedures Plan Year Maximum Per Person Unlimited Orthodontia (Children and Adults) $5 Copay + Fees for Procedures Orthodontic Out - Of - Pocket Max $2,472 Child $3,384 Adult Amounts shown below are your responsibility . Only In - Network benefits are shown For full list of charges, see Patient Charge Schedule GAOV 9 . Dental
 2027 Benefit Guide MPS Page 8 Page 10