
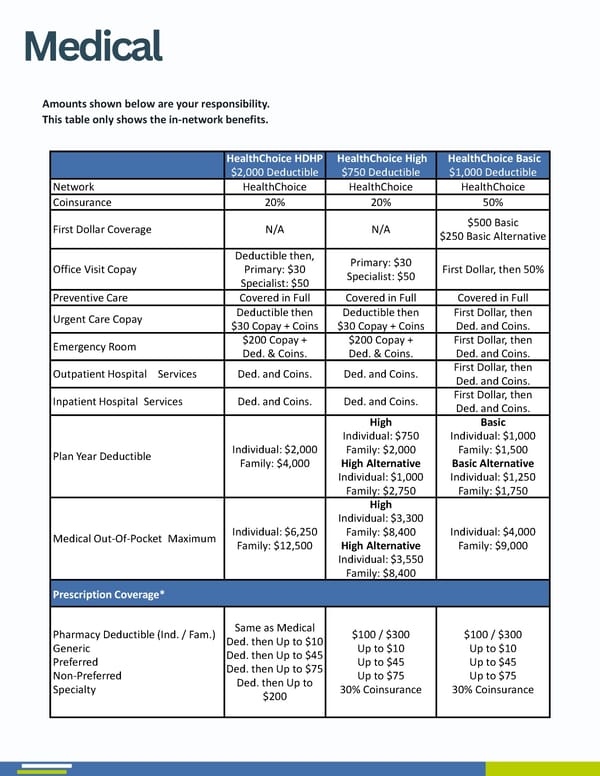
Amounts shown below are your responsibility . This table only shows the in - network benefits . HealthChoice HDHP $2,000 Deductible HealthChoice High $750 Deductible HealthChoice Basic $1,000 Deductible Network HealthChoice HealthChoice HealthChoice Coinsurance 20% 20% 50% First Dollar Coverage N/A N/A $500 Basic $250 Basic Alternative Office Visit Copay Deductible then, Primary: $30 Specialist: $50 Primary: $30 Specialist: $50 First Dollar, then 50% Preventive Care Covered in Full Covered in Full Covered in Full Urgent Care Copay Deductible then $30 Copay + Coins Deductible then $30 Copay + Coins First Dollar, then Ded. and Coins. Emergency Room $200 Copay + Ded. & Coins. $200 Copay + Ded. & Coins. First Dollar, then Ded. and Coins. Outpatient Hospital . Services Ded. and Coins. Ded. and Coins. First Dollar, then Ded. and Coins. Inpatient Hospital . Services Ded. and Coins. Ded. and Coins. First Dollar, then Ded. and Coins. Plan Year Deductible Individual: $2,000 Family: $4,000 High Individual: $750 Family: $2,000 High Alternative Individual: $1,000 Family: $2,750 Basic Individual: $1,000 Family: $1,500 Basic Alternative Individual: $1,250 Family: $1,750 Medical Out - Of - Pocket . Maximum Individual: $6,250 Family: $12,500 High Individual: $3,300 Family: $8,400 High Alternative Individual: $3,550 Family: $8,400 Individual: $4,000 Family: $9,000 Prescription Coverage* Pharmacy Deductible (Ind. / Fam.) Generic Preferred Non - Preferred Specialty Same as Medical Ded. then Up to $10 Ded. then Up to $45 Ded. then Up to $75 Ded. then Up to $200 $100 / $300 Up to $10 Up to $45 Up to $75 30% Coinsurance $100 / $300 Up to $10 Up to $45 Up to $75 30% Coinsurance Medical
 2027 Benefit Guide MPS Page 4 Page 6