
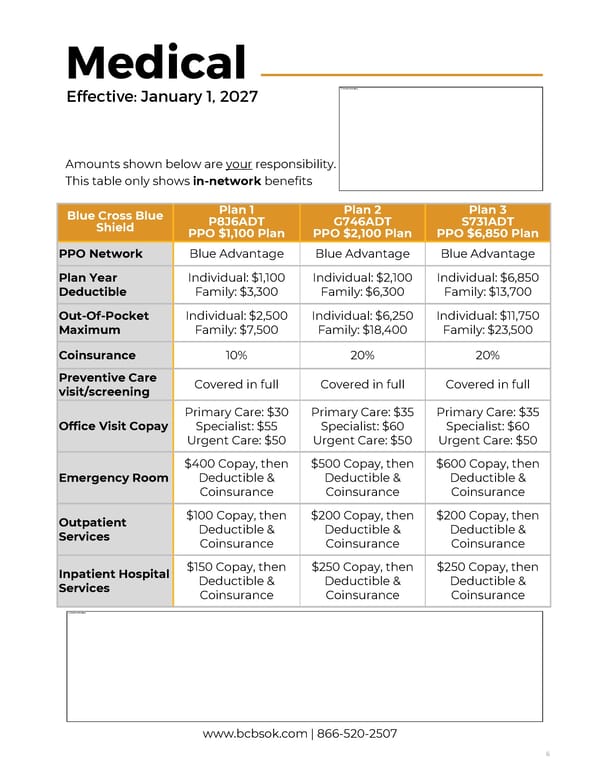
Medical Plan 3 S731ADT PPO $6,850 Plan Plan 2 G746ADT PPO $2,100 Plan Blue Cross Blue Plan 1 P8J6ADT PPO $1,100 Plan Shield PPO Network Blue Advantage Blue Advantage Blue Advantage Individual: $6,850 Individual: $2,100 Family: $13,700 Individual: $1,100 Family: $6,300 Plan Year Deductible Family: $3,300 Individual: $11,750 Individual: $6,250 Family: $23,500 Individual: $2,500 Family: $18,400 Out-Of-Pocket Maximum Family: $7,500 Coinsurance 10% 20% 20% Preventive Care Covered in full Covered in full Covered in full visit/screening Primary Care: $35 Specialist: $60 Urgent Care: $50 Primary Care: $35 Specialist: $60 Urgent Care: $50 Primary Care: $30 Office Visit Copay Specialist: $55 Urgent Care: $50 $600 Copay, then Deductible & Coinsurance $500 Copay, then Deductible & Coinsurance $400 Copay, then Deductible & Emergency Room Coinsurance $200 Copay, then Deductible & Coinsurance $200 Copay, then Deductible & Coinsurance $100 Copay, then Deductible & Coinsurance Outpatient Services $250 Copay, then Deductible & Coinsurance $250 Copay, then Deductible & Coinsurance $150 Copay, then Deductible & Coinsurance Inpatient Hospital Services The picture can't be displayed. Effective: January 1, 2027 Amounts shown below are your responsibility. This table only shows in-network benefits 6 The picture can't be displayed. www.bcbsok.com / 866-520-2507
 2027 Employee Benefits Guide Page 5 Page 7